Blog
How Long Does Semax Injection Take to Work? A Guide


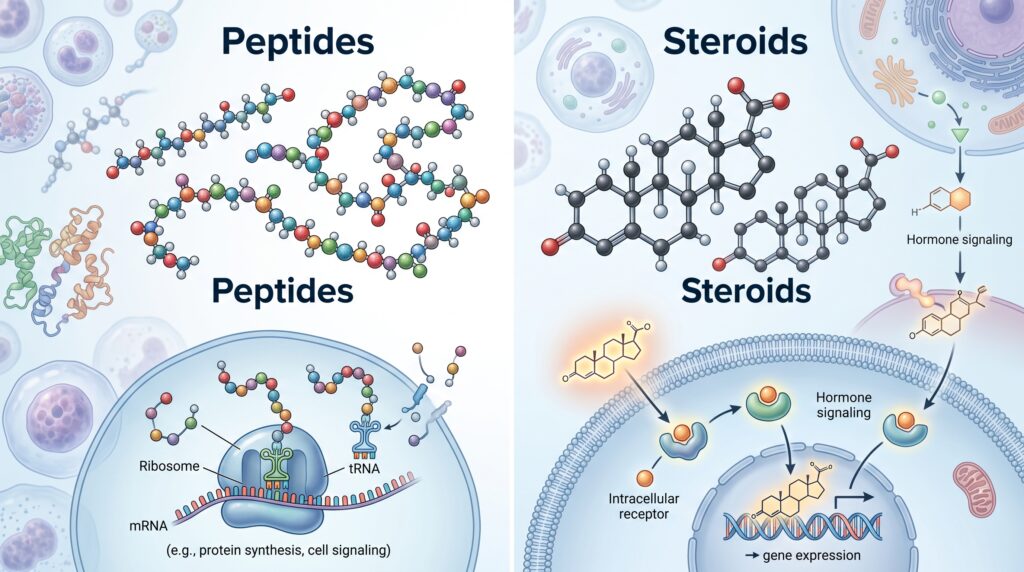
Semax is a synthetic peptide that has attracted considerable attention in both experimental neuroscience and wellness circles due to its potential influence on neurological functions. Originally developed by researchers in Russia during the late twentieth century, this heptapeptide—meaning it consists of a chain of seven amino acids—was designed to mimic a specific fragment of adrenocorticotropic hormone (ACTH) without triggering the typical hormonal responses in the adrenal glands. Over the years, scientists have investigated Semax for its possible neuroprotective, cognitive-enhancing, and adaptogenic properties. In clinical settings within Eastern Europe, it has been explored as an intervention for conditions involving impaired cerebral circulation, cognitive decline, and optic nerve atrophy. Outside of those specific geographic and clinical frameworks, however, Semax has increasingly captured the curiosity of individuals looking for nootropic compounds aimed at sharpening mental clarity, improving memory retention, or accelerating recovery from neurological fatigue.
Because many individuals look to peptides with the hope of achieving noticeable improvements in focus, mood, or cognitive stamina, questions naturally arise regarding the pharmacokinetics of the compound—specifically, how quickly a person might expect to feel or measure its effects and how long those changes remain active in the body. When evaluating any bioactive substance, understanding the onset time and duration of action is essential for gauging both its practical utility and its safety profile. People exploring injectable formulations often assume that bypassing the digestive tract or nasal mucosa will automatically yield a rapid, predictable response. Consequently, prospective users and researchers alike frequently search for a definitive timeline detailing when the compound begins altering brain chemistry and when those alterations translate into tangible cognitive shifts.
Despite the growing public interest in injectable protocols, the scientific reality surrounding injected Semax in human populations remains remarkably sparse. Most of the foundational clinical human data comes from intranasal administration, which is the standard delivery method approved in the limited jurisdictions where Semax is prescribed as a medication. Conversely, data regarding subcutaneous or intramuscular injections of Semax are derived overwhelmingly from rodent models and in vitro laboratory experiments. Because animal metabolism and physiological responses differ substantially from human biology, scientists have not established a reliable, standardized onset time for injected Semax in humans. Anyone evaluating this administration route must contend with significant clinical uncertainty, as well-controlled human pharmacokinetic trials verifying how fast an injection takes effect simply do not exist in major peer-reviewed medical literature.
What Is Semax Injection?
Understanding Semax and Its Proposed Mechanism
At the molecular level, Semax is a synthetic analogue of the ACTH(4-10) fragment, modified with a specific sequence of amino acids—Proline-Glycine-Proline (Pro-Gly-Pro)—attached to its C-terminus. This structural addition was engineered intentionally to resist rapid enzymatic breakdown in the body, thereby extending the biological stability of the peptide compared to natural ACTH fragments. Unlike full-length adrenocorticotropic hormone, Semax does not stimulate the adrenal cortex to release cortisol or other glucocorticoids, allowing researchers to study its direct neurological pathways without introducing systemic endocrine side effects. In injectable form, the peptide is typically supplied as a lyophilized (freeze-dried) powder that must be reconstituted with bacteriostatic or sterile water before being administered subcutaneously or intramuscularly.
The proposed mechanisms through which Semax operates center primarily on its ability to modulate neurotrophic factors and neurotransmitter systems within the central nervous system. Preclinical studies suggest that Semax rapidly upregulates the expression of Brain-Derived Neurotrophic Factor (BDNF) and its corresponding receptor, Tropomyosin receptor kinase B (TrkB), particularly in the hippocampus and basal forebrain. BDNF is a crucial protein responsible for supporting the survival of existing neurons and encouraging the growth, regeneration, and differentiation of new neurons and synapses. Additionally, experimental evidence indicates that Semax influences the activity of dopaminergic and serotonergic systems, potentially altering the turnover and availability of dopamine and serotonin in key brain regions. Researchers also study its capacity to inhibit enkephalin-degrading enzymes, which may play a role in regulating stress responses and pain perception at the cellular level.
How Semax Has Been Studied in Scientific Research
The trajectory of scientific inquiry into Semax has followed two distinct paths: preclinical laboratory investigations in animals and localized clinical trials in human patients within Russia and neighboring countries. In preclinical settings, researchers frequently utilize intraperitoneal or subcutaneous injections in rats and mice to observe how the peptide affects gene expression, cerebral blood flow, and behavioral outcomes under induced stress or simulated ischemic stroke. These animal models allow scientists to examine brain tissue directly after administration, tracking shifts in mRNA levels for neurotrophins and observing cellular survival rates following hypoxic injury. Such experiments have provided valuable insights into how the peptide interacts with cellular signaling cascades, oxidative stress markers, and inflammatory genes inside the mammalian brain.
When shifting to human research, however, the methodology changes noticeably. The vast majority of human trials evaluating Semax have focused on acute ischemic stroke recovery, dyscirculatory encephalopathy, and cognitive impairments, utilizing intranasal drops rather than injections. Furthermore, many of these clinical studies were conducted with relatively small sample sizes and published solely in Russian-language medical journals, sometimes lacking the rigorous double-blind, placebo-controlled methodologies required by Western regulatory agencies like the U.S. Food and Drug Administration (FDA) or the European Medicines Agency (EMA). As a result, while there is an intriguing body of preliminary literature pointing toward neuroprotective potential, the global scientific community views the clinical evidence for Semax—especially in an injectable format—as incomplete and unverified by large-scale international standards.
Differences Between Semax Injection and Nasal Formulations
The primary distinction between injectable Semax and the traditional nasal spray formulation lies in how the peptide enters the body and navigates toward the central nervous system. Intranasal administration was specifically chosen by the original developers of Semax because it takes advantage of the olfactory and trigeminal nerve pathways located in the upper nasal cavity. When applied as nasal drops or a spray, a portion of the small peptide can bypass the blood-brain barrier directly, traveling along perineural spaces into the cerebrospinal fluid and brain tissue within minutes. This direct nose-to-brain transport minimizes systemic circulation exposure, reducing the amount of peptide lost to enzymatic degradation in the bloodstream and peripheral organs.
In contrast, a Semax injection introduces the compound into the subcutaneous fat layer or muscle tissue, requiring the peptide to be absorbed into the systemic capillary network first. Once inside the general bloodstream, the peptide must circulate throughout the body, survive exposure to blood-borne peptidases (enzymes that cleave peptide bonds), and successfully cross the tightly regulated blood-brain barrier to reach its neurological targets. Although the Pro-Gly-Pro tail provides some resistance against rapid proteolysis, systemic circulation presents a much harsher enzymatic environment than direct mucosal transport. Consequently, an injectable route alters the pharmacokinetic profile entirely, changing how much intact Semax actually reaches the brain compared to its cleaved metabolic breakdown products.
How Long Does Semax Injection Take to Work?
What Research Says About the Onset of Effects
When examining the scientific literature for clues regarding the onset of action, it is vital to separate cellular changes observed in laboratory animals from noticeable cognitive or therapeutic effects in humans. In rodent studies where Semax is injected directly into the body, shifts in gene expression—such as the upregulation of BDNF mRNA and changes in immune-related gene transcripts in the brain—have been detected within thirty minutes to a few hours post-administration. Biochemical assays in animal models also indicate that alterations in extracellular dopamine and serotonin metabolite levels can begin occurring within the first hour after an injection, particularly when the animals are subjected to pharmacological challenges or behavioral stress tests.
However, translating these rapid biochemical markers in rodents into a timeline for human perception is scientifically unsound. A spike in neurotrophic factor transcription at the cellular level does not equate to an immediate, perceptible change in human focus, memory, or symptom relief. Structural neuroplasticity, synaptic remodeling, and recovery from neural inflammation are gradual biological processes that unfold over days or weeks rather than minutes. In the limited human studies where Semax was evaluated—almost exclusively via the nasal route—researchers typically assessed clinical outcomes over multi-day or multi-week treatment courses rather than measuring instantaneous cognitive shifts following a single dose. Therefore, current research does not verify a specific minute-by-minute or hour-by-hour onset window for humans utilizing injectable Semax.
Why the Exact Time to Notice Effects Is Unknown
The primary reason medical science cannot provide an exact timeframe for when an injected dose of Semax begins working is the complete absence of formal human pharmacokinetic and pharmacodynamic studies for the parenteral (injected) route. To establish an accurate onset time for any medication, clinical pharmacologists must conduct Phase I trials in healthy volunteers, drawing serial blood and cerebrospinal fluid samples at precise intervals after injection while simultaneously administering standardized neurocognitive assessments. Because injected Semax is not an approved pharmaceutical product in major regulatory jurisdictions, these foundational human trials have never been performed or published in global peer-reviewed literature.
Additionally, defining what it means for a neurological peptide to “work” introduces substantial measurement challenges. Unlike an analgesic that provides a clear transition from pain to relief, or a sedative that induces measurable drowsiness, compounds studied for neuroprotection or subtle cognitive modulation often produce effects that are difficult to quantify subjectively. An individual may not consciously feel an increase in neurotrophic signaling or mild shifts in neurotransmitter turnover. When anecdotal reports online describe rapid effects after an injection, it is impossible for clinicians to distinguish genuine pharmacological action from the placebo effect, heightened anticipation, or natural fluctuations in daily energy and alertness.
How Administration Methods May Affect Absorption
The physical method by which a substance is introduced into the body dictates its absorption rate, bioavailability, and peak plasma concentration. When a medication is injected subcutaneously, it forms a small depot within the interstitial tissue beneath the skin. From there, the molecules must diffuse across capillary membranes or enter the lymphatic system to reach general circulation. The speed of this absorption depends on local blood flow, tissue temperature, the molecular weight of the compound, and the volume of liquid injected. While small water-soluble peptides generally absorb relatively quickly from subcutaneous tissue into the bloodstream—often reaching systemic circulation within fifteen to thirty minutes—reaching the bloodstream is only the first step.
Once in the vascular system, the rate at which Semax exerts central nervous system effects is governed by blood-brain barrier permeability and enzymatic stability. Serum peptidases immediately begin breaking down the seven-amino-acid chain into smaller fragments, which may possess different biological activities or none at all. In contrast, intranasal delivery deposits the peptide directly onto the olfactory epithelium, offering a shorter physical path to cerebral tissues without first diluting the dose across several liters of systemic blood. Because the absorption kinetics, enzymatic exposure, and transport barriers differ so markedly between subcutaneous tissue and nasal mucosa, one cannot assume that an injection will act faster or more potently than a nasal formulation.
What Factors May Influence Semax’s Effects?
Individual Differences in Response
Even if standardized human protocols existed for injectable Semax, biological variability among individuals would cause noticeable differences in how the peptide is processed and experienced. Human neurochemistry is highly individualized, shaped by genetic variations that govern receptor density, baseline neurotransmitter synthesis, and enzymatic activity. For instance, polymorphisms in the gene responsible for producing BDNF (such as the well-studied Val66Met variant) can significantly alter how effectively a person’s brain secretes and responds to neurotrophic factors. Because Semax is proposed to work largely through the BDNF/TrkB signaling pathway, genetic differences in this system could theoretically render one person highly responsive at the cellular level while leaving another largely unaffected.
Beyond genetics, an individual’s baseline physiological and neurological state plays a critical role in how neuromodulatory compounds behave. Research in animal models frequently demonstrates that the effects of Semax are state-dependent; the peptide often produces pronounced biochemical corrections in brains subjected to ischemia, oxidative stress, or acute fatigue, while showing minimal measurable impact in healthy, unstressed control animals. Factors such as age, metabolic rate, sleep quality, nutritional status, and chronic stress levels also influence blood-brain barrier integrity and systemic enzyme activity, creating a complex web of variables that would modify both the onset and magnitude of any potential biological response.
Formulation Quality and Product Purity
In the absence of regulated pharmaceutical manufacturing for injectable Semax, product quality stands out as one of the most significant variables influencing what happens when a person administers a dose. Outside of approved clinical nasal formulations in Russia, almost all injectable Semax acquired by consumers comes from unregulated online vendors marketing compounds labeled as “research chemicals” or “not for human consumption.” These products are synthesized by third-party laboratories that are not subject to routine inspections or Current Good Manufacturing Practice (cGMP) standards enforced by health authorities. Consequently, the actual content of a vial labeled as Semax can vary wildly from one batch to the next.
Analytical testing of unregulated peptides frequently reveals concerning discrepancies, including severe under-dosing, over-dosing, or the complete absence of the stated active ingredient. Furthermore, improper synthesis or storage can lead to peptide degradation, oxidation, or misfolding, rendering the amino acid chain biologically inactive before it is ever reconstituted. Peptide bonds are delicate; exposure to heat during shipping or vigorous shaking during reconstitution can shear the molecular structure. If a product contains degraded peptide fragments or synthesis impurities, any anticipated pharmacological effect will be altered, delayed, or entirely absent, while the risk of adverse immune reactions increases substantially.
The Importance of Medical History and Other Medications
An individual’s underlying medical history and concurrent medication regimen can profoundly alter how a bioactive peptide interacts with the body. Because Semax is believed to modulate dopaminergic and serotonergic signaling pathways, its activity may overlap or clash with prescription psychiatric or neurological medications. For example, individuals taking selective serotonin reuptake inhibitors (SSRIs), monoamine oxidase inhibitors (MAOIs), stimulants, or dopamine agonists already have artificially altered neurotransmitter dynamics in their synaptic clefts. Introducing an uncharacterized peptide that influences these same monoamine systems could theoretically blunt expected effects, amplify nervous system overstimulation, or trigger unpredictable neurochemical imbalances.
Systemic health conditions also influence peptide pharmacokinetics. Kidney and liver function dictate how efficiently metabolic byproducts and cleaved amino acid fragments are cleared from the bloodstream, while cardiovascular health and microvascular integrity determine how effectively blood circulates to peripheral tissues and the brain. Chronic inflammatory conditions, autoimmune disorders, or endocrine imbalances may further shift how the immune system reacts to an exogenous injected peptide. Without a thorough evaluation of a patient’s medical background and existing prescriptions, predicting how the body will metabolize or respond to an experimental compound is clinically impossible.
How Long Do the Effects of Semax Last?
What Is Known About the Duration of Its Effects?
Understanding how long Semax remains active in the body requires looking at the paradox between its biological half-life in the bloodstream and its downstream cellular effects. In laboratory tests measuring intact peptide stability in biological fluids, Semax has a remarkably short plasma half-life—often measured in mere minutes once exposed to blood enzymes. Peptidases rapidly cleave the heptapeptide into smaller fragments, including hexapeptides, pentapeptides, and the terminal Pro-Gly-Pro tripeptide. If one were judging duration solely by how long the intact parent molecule circulates in the blood, the expected duration of action would appear fleetingly brief.
However, preclinical research suggests that the functional effects of Semax outlast its presence in plasma by several hours. Studies in animals indicate that even after the intact peptide is degraded, some of its stable breakdown products—particularly the Pro-Gly-Pro fragment—retain biological activity of their own, continuing to influence cerebral circulation and cellular signaling. Furthermore, in Russian medical literature describing intranasal administration, researchers have noted that physiological and neuroprotective effects can persist for twenty to twenty-four hours following administration. Nevertheless, whether an injectable dose in humans mirrors this twenty-four-hour functional window remains unverified by modern clinical trials.
Why Duration May Differ From Onset Time
In pharmacology, the time it takes for a compound to initiate a biological process is governed by entirely different mechanisms than the time required for those effects to wear off. Onset time is primarily a function of absorption kinetics, tissue distribution, and initial receptor binding. Once Semax reaches its target tissues in the brain and interacts with melanocortin receptors or allosteric sites on neurotrophin receptors, it acts like a biological switch, triggering intracellular signaling cascades and altering gene transcription. The initial engagement of that switch may happen relatively quickly once the molecule crosses into the central nervous system.
The duration of the effect, on the other hand, is determined by how long those newly synthesized proteins, upregulated receptors, and altered neurotransmitter levels remain active inside the neurons. When Semax stimulates the transcription of BDNF mRNA, the cell produces neurotrophic proteins that promote synaptic plasticity and cellular resilience over an extended period, long after the original Semax molecule has been completely broken down and excreted from the body. This secondary messenger cascade explains why a peptide with a biological half-life of only a few minutes in the blood can theoretically trigger biochemical ripples that last for hours or days, separating the concept of initial onset from total duration.
Limitations of Available Human Research
While the theoretical mechanisms explaining prolonged duration are compelling in laboratory settings, major limitations in available human research prevent clinicians from stating definitively how long Semax lasts in practice. First, there is no consensus on how to measure the end of the peptide’s effect in humans. In stroke recovery trials, improvements in neurological function are intended to be permanent healing outcomes rather than temporary drug effects that wear off after a few hours. Conversely, in healthy individuals seeking temporary cognitive enhancement, there are no standardized, large-scale human trials tracking cognitive test scores hour-by-hour over a twenty-four-hour cycle after an injection to chart a clear rise and fall in performance.
Second, the vast majority of published data comes from specific patient populations—such as older adults recovering from cerebrovascular events or individuals with chronic optic nerve damage—whose baseline neurological functioning is severely compromised. Extrapolating duration data from an ischemic stroke patient receiving multi-day intranasal therapy in a hospital setting to a healthy adult self-administering a subcutaneous injection is scientifically invalid. Without rigorous pharmacokinetic mapping in diverse human cohorts, any claims specifying an exact number of hours for the duration of injected Semax remain speculative.
What Does Scientific Research Say About Semax?
Research on Cognitive Function and Memory
The scientific exploration of Semax regarding memory and cognition originated with behavioral experiments in rodents. In numerous preclinical trials, rats administered Semax demonstrated improved learning capacity in maze navigation tests, enhanced passive avoidance memory, and greater resistance to amnesia induced by electroconvulsive shock or oxygen deprivation. Researchers observed that the peptide appeared to facilitate the consolidation of information and improve attention span during complex tasks, effects that correlated strongly with increased BDNF expression and elevated cholinergic and dopaminergic activity in the hippocampus and prefrontal cortex.
A limited number of early human studies conducted in Russia attempted to evaluate whether these cognitive benefits extended to healthy human workers. In small-scale tests involving healthy volunteers—including operators working under high-stress conditions or fatigue after extended shifts—intranasal Semax was reported to improve attention, short-term memory accuracy, and mental work capacity compared to baseline measurements. However, these studies involved very small participant numbers, utilized non-standardized cognitive testing batteries, and lacked independent replication by international research teams. Consequently, while preliminary data suggest an intriguing connection between Semax and memory maintenance under fatigue, definitive proof of cognitive enhancement in healthy humans remains elusive.
Studies Investigating Neurological Effects
The strongest focus of clinical Semax research in Eastern Europe has centered on acute neurological pathology, particularly ischemic stroke and chronic cerebrovascular insufficiency. During an ischemic stroke, a blockage in blood flow deprives brain tissue of oxygen and glucose, triggering a destructive cascade of glutamate excitotoxicity, oxidative stress, local inflammation, and neuronal apoptosis (cell death). Russian clinical trials have investigated high-dose intranasal Semax administered within the first hours or days following a stroke to see if it can salvage vulnerable brain tissue in the ischemic penumbra.
Findings from these localized clinical studies suggest that patients treated with Semax alongside standard care exhibited faster functional recovery, reduced mortality rates, and elevated plasma levels of BDNF compared to control groups. Additional studies have explored its application in ophthalmology, specifically for glaucomatous optic neuropathy and optic nerve atrophy, where researchers reported improvements in visual field parameters and retinal electrical activity. In laboratory models, Semax has also been shown to suppress the activation of pro-inflammatory genes while stimulating anti-inflammatory and vascular growth pathways after brain injury. Despite these promising signals, international neurological guidelines do not currently recognize Semax as a standard-of-care treatment due to methodological gaps in the underlying trials.
Limitations of Current Evidence
A critical evaluation of the scientific literature surrounding Semax reveals substantial methodological limitations that prevent mainstream medical adoption. A primary concern among global researchers is publication bias and lack of geographic diversity; nearly the entire body of clinical human research originates from a narrow network of institutions in Russia where the peptide was originally patented and commercialized. Independent, multi-center randomized controlled trials conducted in North America, Western Europe, or East Asia are virtually non-existent, meaning the reported clinical outcomes have not undergone external verification under international Good Clinical Practice (GCP) standards.
Furthermore, many of the foundational studies suffer from small sample sizes, inadequate blinding procedures, and poorly defined primary endpoints. When evaluating injectable Semax specifically, the evidence gap widens into a chasm: there are essentially no peer-reviewed clinical trials assessing subcutaneous or intramuscular Semax for cognitive enhancement or neurological treatment in human beings. Relying on rodent injection data or human nasal drip studies to justify injectable protocols overlooks fundamental principles of evidence-based medicine, leaving critical questions about human dosing, long-term efficacy, and systemic pharmacology unanswered.
Is Semax Injection Safe?
Potential Side Effects and Unknown Risks
Because injectable Semax has not undergone formal safety testing in humans, its comprehensive side effect profile remains unknown. In Russian medical literature detailing intranasal use, the peptide is generally described as well-tolerated, with the most common adverse effect being mild irritation or discoloration of the nasal mucosa during prolonged use. However, injecting a substance subcutaneously or intramuscularly introduces entirely different physiological variables and potential reactions. Common local risks associated with any peptide injection include redness, swelling, itching, pain, bruising, or the formation of sterile abscesses and subcutaneous nodules at the injection site.
Systemically, anecdotal reports and theoretical pharmacological considerations point toward several potential side effects, including headaches, transient spikes or drops in blood pressure, heightened anxiety, restlessness, insomnia, and hair shedding (which some researchers hypothesize may relate to chronically elevated BDNF levels influencing hair follicle cycling, as BDNF plays a role in regulating the transition from the growth phase to the resting phase of hair follicles). More importantly, the long-term risks of repeatedly injecting a synthetic neuropeptide are completely unmapped. Scientists do not know whether chronic systemic exposure to Semax could cause receptor downregulation, desensitization of endogenous neurotrophic pathways, autoimmune antibody formation against the peptide, or unforeseen metabolic complications over months and years.
Concerns About Unregulated Peptide Products
For individuals outside of jurisdictions where pharmaceutical nasal Semax is legally dispensed, the greatest immediate danger comes not necessarily from the Semax molecule itself, but from the unregulated gray-market supply chain. Injectable Semax vials sold online are manufactured without regulatory oversight, meaning there is no guarantee of sterility, apyrogenicity, or chemical purity. When a compound is injected past the skin’s protective barrier, any contaminants inside the vial are delivered directly into the body’s internal tissues and bloodstream.
Laboratory analyses of illicitly sold injectable peptides have uncovered alarming hazards, including bacterial contamination, fungal spores, and high levels of bacterial endotoxins (pyrogens) that can trigger severe systemic inflammatory reactions, high fevers, or life-threatening sepsis. Additionally, chemical synthesis of peptides utilizes toxic solvents and heavy metal catalysts, such as trifluoroacetic acid (TFA) and DMF; if the laboratory fails to perform rigorous purification and lyophilization steps, toxic chemical residues remain in the powder. Injecting unpurified trifluoroacetic acid salts or improperly reconstituted solutions can cause localized tissue necrosis and systemic organ toxicity.
Why Medical Supervision Is Important
Attempting to self-administer an experimental neuroactive compound via injection without qualified medical supervision carries substantial health hazards. A licensed healthcare professional does far more than simply write prescriptions; they evaluate a patient’s symptoms through diagnostic testing to identify the root cause of cognitive fatigue, memory issues, or neurological complaints. Symptoms such as brain fog, poor concentration, or low mood frequently stem from treatable medical conditions—such as thyroid dysfunction, vitamin deficiencies, sleep apnea, chronic infections, or vascular disease—that require targeted, evidence-based medical care rather than unverified peptides.
Furthermore, medical supervision ensures that if a patient is participating in a legitimate clinical trial or receiving an approved therapy, their vital signs, blood chemistry, and neurological status are closely monitored for early signs of adverse reactions. Self-experimentation removes this critical safety net. Without clinical oversight, an individual runs the risk of miscalculating reconstitution math, using improper sterile injection techniques that introduce skin bacteria into deep tissues, or ignoring subtle warning signs of systemic toxicity or drug interactions until a medical emergency occurs.
Is Semax Injection Approved for Medical Use?
Differences in Regulatory Status Between Countries
The legal and regulatory status of Semax varies sharply depending on international borders. In the Russian Federation and a handful of neighboring Eastern European nations, Semax has been approved for clinical use since the late 1990s and is listed on the Russian Registry of Vital and Essential Drugs. However, it is crucial to note that even in Russia, the approved pharmaceutical product is marketed exclusively as a 0.1% or 1% intranasal drop solution intended for specific neurological and ophthalmic diagnoses; an injectable formulation is not the standard commercial clinical product.
In contrast, major global regulatory bodies—including the U.S. Food and Drug Administration (FDA), the European Medicines Agency (EMA), Health Canada, and the Australian Therapeutic Goods Administration (TGA)—have never approved Semax in any formulation, whether nasal or injectable, for human medical use. In the United States, the FDA has specifically placed Semax on lists of bulk drug substances that present significant safety risks or lack sufficient clinical data to be used in pharmacy compounding. Consequently, in most parts of the world, Semax cannot be legally prescribed, marketed, or dispensed as a conventional pharmaceutical medication or dietary supplement.
Research Use Versus Established Medical Treatment
To navigate the landscape of experimental peptides safely, it is essential to understand the strict legal and scientific boundary between a “research chemical” and an established medical treatment. Before a drug can be classified as an established medical treatment, the manufacturer must submit an Investigational New Drug (IND) application, conduct phased clinical trials involving thousands of human participants to prove both safety and efficacy for a specific condition, and undergo exhaustive manufacturing inspections. Only after clearing these rigorous hurdles is a medication granted marketing authorization for human patients.
Compounds sold online with labels stating “For Research Use Only” or “Not for Human Consumption” belong to a completely different category. Legally, these chemicals are intended solely for in vitro laboratory experiments, chemical analysis, or approved institutional animal studies. Vendors often use this labeling to bypass pharmaceutical regulations while implicitly marketing to consumers interested in self-experimentation. A research-grade chemical is not held to human pharmaceutical purity or sterility standards, and purchasing a reagent intended for a test tube or laboratory rodent to inject into the human body crosses a dangerous line between laboratory science and unregulated human experimentation. How long does semax injection take to work
How to Evaluate Medical Claims About Semax
Patients and consumers looking into Semax online are frequently confronted with bold marketing claims from wellness blogs, biohacking forums, and peptide clinics asserting that the compound effortlessly boosts intelligence, repairs brain damage, or eliminates anxiety within minutes of injection. Evaluating these claims requires a healthy dose of scientific skepticism and media literacy. A primary red flag is any definitive statement promising a guaranteed onset time, a specific percentage increase in cognitive performance, or a universal dosage chart for human injections, as none of those claims are backed by peer-reviewed human clinical trials.
When assessing medical information about Semax, readers should look directly at the source of the evidence being cited. Often, commercial websites cite a study showing neuroprotection or rapid BDNF elevation while omitting the fact that the study was performed on severed rat brain tissue in a Petri dish or involved rodents injected prior to induced brain trauma. Reliable medical sources clearly distinguish between preclinical animal models and human clinical outcomes, openly acknowledge the limitations of small single-country studies, and never promote the self-administration of unapproved injectable research chemicals.
Semax Injection vs. Semax Nasal Spray
Differences in Administration and Absorption
Comparing Semax injection to Semax nasal spray highlights how drastically the route of administration dictates the journey of a drug inside the body. The intranasal spray or drop method is non-invasive and relies on depositing the peptide across the highly vascularized nasal mucosa and the olfactory region at the roof of the nasal cavity. This location provides a unique anatomical shortcut: peptides can travel paracellularly or transcellularly along the olfactory and trigeminal nerves directly into the central nervous system, bypassing the peripheral bloodstream and the restrictive tight junctions of the blood-brain barrier. However, nasal absorption can be inconsistent if the user has nasal congestion, mucosal inflammation, or improper administration technique that causes the liquid to drip down the throat and get destroyed by stomach acid.
An injection bypasses mucosal barriers entirely by placing the dissolved peptide directly beneath the skin or into muscle tissue, ensuring that 100% of the administered liquid enters the body’s internal tissue spaces. While this eliminates the issue of nasal drip or sinus congestion, it introduces the challenge of systemic enzymatic degradation. Once absorbed into peripheral capillaries, the injected peptide is diluted throughout the entire circulatory system and exposed to serum proteases before a tiny fraction can attempt to cross the blood-brain barrier from the vascular side. Thus, while an injection guarantees systemic entry, it does not necessarily guarantee superior delivery to the brain tissue itself.
What Evidence Is Available for Each Formulation?
When weighing the scientific literature supporting each delivery method, the disparity in human evidence is striking. The intranasal formulation is supported by decades of clinical usage and published human trials within Russia, covering hundreds of patients treated for ischemic stroke, transient ischemic attacks, dyscirculatory encephalopathy, and optic nerve disorders. Pharmacokinetic models and clinical dosing guidelines in Russian medical references are built exclusively around intranasal delivery, as researchers specifically optimized the peptide’s concentration and volume for mucosal absorption.
Conversely, the body of evidence for injectable Semax is confined almost entirely to preclinical animal models. Scientists conducting laboratory research on rats or mice frequently choose intraperitoneal or subcutaneous injections simply because it is practically difficult to administer precise, repeatable nasal drops to a small, uncooperative rodent without anesthesia. Therefore, the prevalence of injections in animal literature reflects a practical convenience for laboratory handling rather than a finding that injections are clinically superior for humans. There is no body of peer-reviewed human literature validating the safety, bioavailability, or efficacy of injected Semax.
Why Results From One Formulation Cannot Automatically Apply to Another
A common misconception in self-experimentation communities is that if a compound demonstrates beneficial properties via one administration route, injecting it will simply produce a stronger or faster version of the exact same result. In clinical pharmacology, however, changing the route of administration effectively creates a different therapeutic profile with distinct risks and kinetics. When Semax is administered intranasally, its systemic blood levels remain relatively low while localized concentrations near the olfactory bulb and cerebral fluid rise rapidly. When injected subcutaneously, peripheral organs, blood vessels, and systemic immune cells are exposed to much higher concentrations of the peptide and its breakdown fragments.
Furthermore, because blood-brain barrier transport mechanisms are saturable and selective, flooding the peripheral bloodstream via an injection does not guarantee that a proportional amount will cross into the brain. The enzymatic cleavage pattern in human blood may also differ in speed and proportion from the cleavage pattern in nasal mucus, potentially yielding a different ratio of intact Semax to Pro-Gly-Pro fragments reaching neurological receptors. Because of these profound physiological differences, safety findings, onset estimates, and clinical outcomes observed with nasal drops cannot be automatically extrapolated to subcutaneous or intramuscular injections.
FAQ
How long does Semax injection take to work?
There is no scientifically established or verified timeframe for how long a Semax injection takes to work in humans. While animal studies indicate that biochemical shifts—such as changes in neurotrophic gene expression and neurotransmitter turnover in rodent brains—can begin within thirty to sixty minutes after an injection, no formal human clinical trials have mapped the onset of cognitive or therapeutic effects for the injectable form.
Can Semax produce immediate effects?
From a cellular perspective, preclinical laboratory models show that Semax begins interacting with receptors and altering mRNA transcription relatively quickly after reaching brain tissue. However, in terms of noticeable human symptoms or cognitive enhancement, immediate effects are not scientifically substantiated. Structural brain changes, neuroprotection, and synaptic support are gradual biological processes, and reports of instantaneous mental clarity immediately following an injection cannot be separated from placebo responses without controlled human trials.
How long may Semax’s effects last?
In the bloodstream, the intact Semax molecule has a very short biological half-life of only a few minutes before enzymes break it down into smaller amino acid fragments. Despite this rapid breakdown, research on intranasal formulations suggests that downstream cellular effects and active metabolic byproducts may continue influencing neurological pathways for up to twenty to twenty-four hours. Whether an injected dose in humans follows this same duration timeline remains unproven due to a lack of human pharmacokinetic data.
Is injected Semax better studied than nasal Semax?
No, injected Semax is significantly less studied in humans than the nasal formulation. Almost all human clinical trials conducted in Russia and Eastern Europe have utilized intranasal drops or sprays, which is the only formulation approved for medical use in those regions. Injectable Semax has been studied primarily in laboratory rodents and cell cultures, meaning human safety and efficacy data for injections are virtually non-existent.
Is it safe to use Semax without medical supervision?
Using injectable Semax without medical supervision is not considered safe. Aside from the lack of human safety trials for the injectable route, products sold online as injectable peptides are unregulated research chemicals that do not undergo pharmaceutical quality control. Self-administering these products carries serious risks of bacterial contamination, toxic chemical residues, improper dosing, adverse drug interactions, and unexpected neurological or systemic side effects.
Conclusion
The question of how long a Semax injection takes to work ultimately highlights the wide gap between online curiosity and established medical science. While both the onset time and duration of action are critical parameters for any bioactive compound, neither has been reliably determined for injected Semax in human populations. Although animal experiments demonstrate that cellular signaling and BDNF expression can shift within an hour of a parenteral dose and persist through downstream cascades for several hours, human biology is far too complex to assume those laboratory timelines apply directly to people. Without rigorous human pharmacokinetic trials, any specific timeframe attached to injectable Semax remains purely speculative.
It is equally important to recognize the fundamental distinction between preliminary experimental findings and proven clinical benefits. While the scientific mechanisms surrounding Semax—such as neurotrophic upregulation, modulation of monoamine neurotransmitters, and protection against oxidative stress—offer fascinating avenues for neurological research, early preclinical promise does not equate to a validated, safe human therapy. Relying on rodent studies or localized intranasal stroke trials to justify self-injecting an unapproved research chemical overlooks essential principles of pharmacology and patient safety, particularly given the severe contamination and purity risks associated with unregulated gray-market peptide vials.
Anyone experiencing cognitive difficulties, persistent mental fatigue, memory concerns, or neurological symptoms should prioritize safe, evidence-based care by consulting a qualified healthcare professional. A physician can perform comprehensive diagnostic evaluations to uncover the root causes of cognitive or neurological changes and recommend treatments that have been thoroughly vetted for human safety, purity, and effectiveness. Before considering any unapproved peptide product or experimental protocol, seeking professional medical guidance remains the safest and most responsible course of action for protecting long-term neurological and systemic health.